
This is general information rather than medical advice. Any open pressure wound should be assessed by a clinician or wound care nurse.
A pressure ulcer is damage to the skin and the tissue underneath it, caused by sustained pressure cutting off blood supply, usually over a bony area, usually somewhere that carries weight for hours at a time.
You’ll see them called pressure ulcers, pressure injuries, and bed sores. All three refer to the same thing, and clinicians mostly use pressure injury now because damage can be present before any skin has broken.
This is about what to do once one has formed. If nothing has opened yet, preventing bedsores is the more useful place to start.
The Stages
The National Pressure Injury Advisory Panel classifies these by depth of tissue damage.
Stage 1.
Intact skin with non-blanchable redness. Press it, and the color doesn’t go pale and return. On darker skin, the color change may not be visible at all, so temperature and firmness are the things to go by.
Stage 2.
Partial thickness loss with the dermis exposed. A shallow open wound or a blister.
Stage 3.
Full thickness skin loss, with fat visible in the wound. Often looks like a crater, and there may be considerably more damage tunneling under the edges than the surface suggests.
Stage 4.
Full-thickness loss with muscle, tendon, ligament, cartilage, or bone exposed or able to be felt.
Unstageable.
Full thickness damage where the base is covered by slough or eschar, so the depth can’t be assessed until that’s removed.
Deep tissue pressure injury.
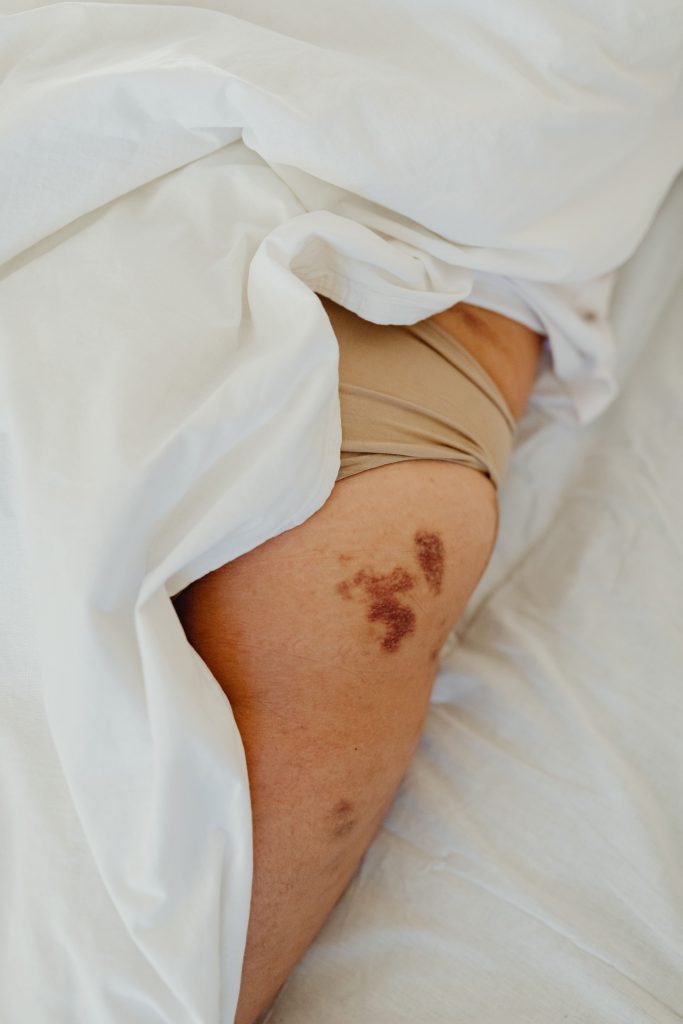
Persistent non-blanchable deep red, maroon, or purple discoloration over intact skin. This one is deceptive and worth knowing about, because it indicates damage happening underneath while the surface still looks closed.
Staging Is Not a Timeline
This is the single most misunderstood thing about pressure ulcers, and almost nothing written for patients says it.
A pressure ulcer does not start at stage 1 and progress upward. Clinical guidance is explicit that the first visible sign can be a deep, necrotic stage 3 or 4 wound. In a rapidly developing injury, the tissue underneath can die before the surface breaks at all, which means a small opening may sit on top of extensive damage below.
So the size of what you can see tells you very little.
And it doesn’t run backward either. A healing stage 4 doesn’t become a stage 3 and then a stage 2. It stays classified as a stage 4 that’s healing, because the tissue that was lost doesn’t regenerate in reverse.
Two practical consequences. A small wound on someone with limited sensation deserves professional assessment rather than a plaster. And if a clinician tells you a wound has been reclassified downward as it heals, that’s not how staging works.
The First Thing, Always
Get all pressure off the area, starting immediately and continuing until it has fully healed.
Not most of the pressure. Not most of the time. A few minutes of weight on a healing wound undoes days of progress, which means rethinking positions, cushions, transfers, and schedules around avoiding that one spot entirely.
Everything else in this article is secondary to that.
What Can Be Managed at Home
Stage 1.
Keep the area clean, dry and completely free of pressure. That’s usually the whole treatment, and at this stage it genuinely works. If it hasn’t resolved after a couple of days of full offloading, call somebody.
Stage 2.
A gentle rinse with saline or mild soap and water, patted dry, and a clean dressing. Current guidance recommends a silicone foam dressing for a non-infected wound with balanced moisture, though hydrocolloid and transparent film dressings are also used. Change as directed and look at the wound properly every time.
Anything deeper than that is not a home care situation, and treating it as one is how people end up in hospital.
Stage 3 and Stage 4
This is the part most consumer articles skip, which leaves people frightened and without information at exactly the point they need it.
Debridement.
Removal of dead tissue, because a wound cannot close over it. This can be surgical, enzymatic, autolytic using dressings that let the body do it, or mechanical. Which method suits depends on the wound, and it’s a clinical decision rather than a preference.
One important exception. Stable, dry eschar should not be debrided purely to work out what stage the wound is. That hard, dry covering is sometimes doing a protective job, and removing it for the sake of classification can make things worse.
Negative pressure wound therapy.
A wound vac. Suction is applied through a sealed dressing, which draws out drainage, increases blood flow, and pulls the wound edges together. It’s used for stage 3 and 4 wounds once the wound has been debrided to a clean base and is free of acute infection. It isn’t used over untreated cellulitis, osteomyelitis,s or an exposed artery.
Reconstructive surgery.
For deep wounds, particularly in people with spinal cord injuries, flap surgery may be the best option rather than the last resort. Tissue from a nearby area is moved to cover the wound and secured in place. Recovery involves an extended period of complete offloading, which is its own logistical problem.
Bone infection.
Stage 4 wounds that reach bone can cause osteomyelitis, which needs antibiotics, sometimes surgical debridement, and occasionally hyperbaric oxygen. This is the complication that turns a wound into a months-long medical situation.
Four Things Not to Do
Don’t massage the area. It was standard advice for decades, es and it damages already compromised tissue.
Don’t use a donut or ring cushion. The raised edge concentrates pressure in a circle around the wound and restricts circulation to exactly the area trying to heal. That’s covered further in the piece on choosing a cushion that actually works.
Don’t expect a routine wound culture to mean much. Every pressure ulcer is heavily colonized with bacteria, so swabbing one and finding organisms tells you almost nothing. Culture is for suspected infection, not for routine monitoring.
Don’t let it dry out completely, or sit wet. Wound healing needs balanced moisture. Too dry and cells can’t migrate across; too wet and the surrounding skin breaks down.
Healing Needs Fuel, and the Targets Are Specific
You cannot build tissue out of nothing, and undernutrition is one of the most common reasons a wound stalls.
Wound healing guidance recommends around 30 to 35 calories per kilogram of body weight per day, and 1.25 to 1.5 grams of protein per kilogram per day; where intake is insufficient for most people, that’s substantially more protein than they’re eating.
Worth knowing that blood markers like albumin and prealbumin aren’t reliable on their own for assessing nutritional status, so a normal result doesn’t mean nutrition isn’t the problem. A proper assessment is a conversation and an examination rather than a blood test.
Fluids matter too, and so do overall calories, because a body short of energy will break down tissue rather than build it.
When to Get Help the Same Day
Any open wound on somebody with limited mobility or sensation warrants a call. These are the signs that shouldn’t wait for an appointment.
Fever or chills. Redness or warmth spreading outward from the wound. Swelling. Pus or cloudy drainage. A foul smell. Black or grey tissue in or around the wound.
All of those point toward infection, and infection in a pressure wound can progress to sepsis quickly.
Slower signs that still need a call: a stage 1 area that hasn’t faded after a couple of days of complete offloading, a wound getting larger rather than smaller, and anything deep enough to show fat, muscle, or bone.
And if your injury is at T6 or above, a wound is a common trigger of autonomic dysreflexia. Sudden pounding headache, sweating or flushing above the injury level, and a slowed heart rate all warrant immediate attention.
How Long This Takes
Longer than anybody wants to hear.
A stage 1 area that’s caught early can resolve in days. Stage 2 wounds often heal in weeks with consistent offloading and dressing changes. Stage 3 and 4 wounds are measured in months, and a deep wound with complications can run past a year.
Which is why the offloading discipline matters so much. Every episode of pressure on a healing wound resets progress, and the arithmetic of a months-long recovery is brutal when a single afternoon of sitting wrong can cost weeks.
Healed skin also stays weaker than it was. Once you’ve had a wound in a particular spot, that spot needs watching permanently.
Catch It Earlier Next Time
Almost every pressure ulcer at stage 3 or 4 was a stage 1 that somebody missed, or saw and didn’t act on fast enough.
Daily skin checks, weight shifts on a schedule, a cushion that still works, and acting on the first discolored patch rather than waiting to see. That’s the whole prevention picture, and it’s in the companion piece on preventing bed sores.




4 Comments